Cms-1490S Printable Form
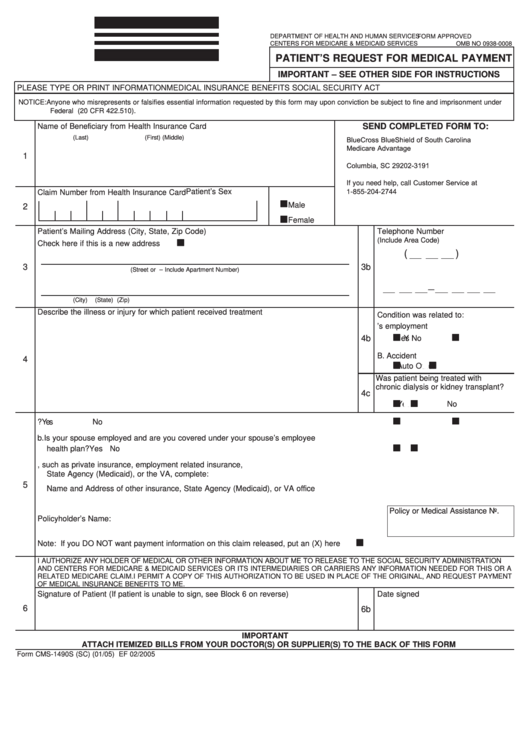
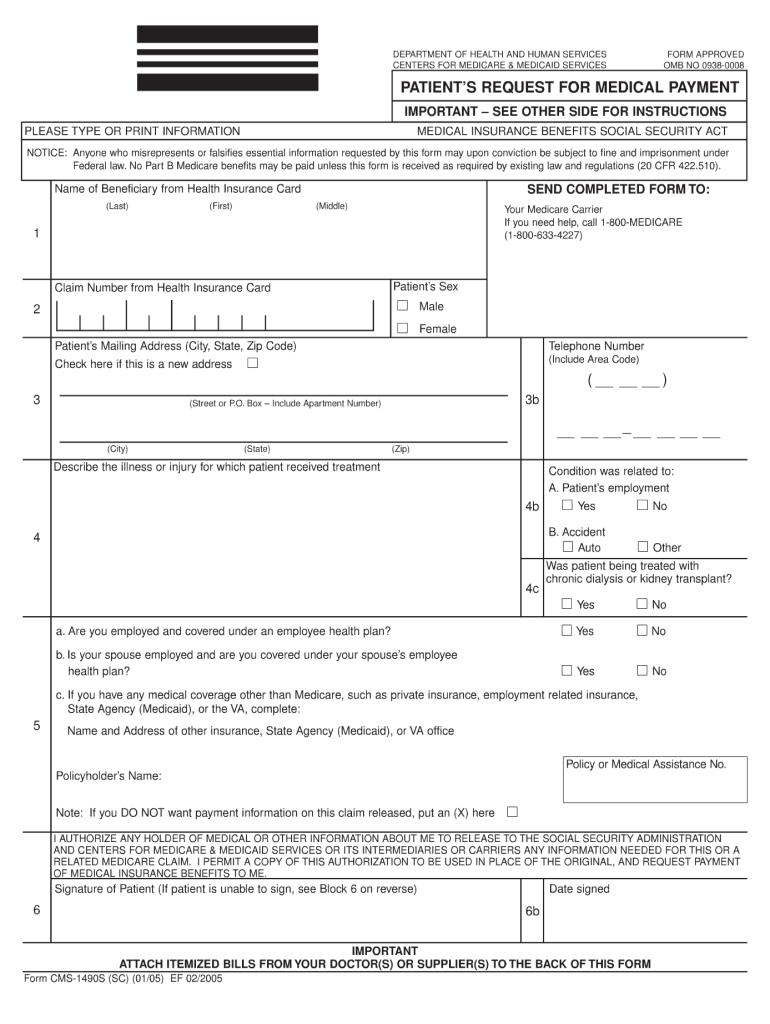
Cms-1490S Printable Form - Medical forms · ds 11 form · for business Web view / download form. For all claims including influenza and pneumococcal vaccinations,. • name, medicare number, and address •. Web mail your completed claim form to the medicare carrier responsible for processing your claim. Send the form to the. Please read all instructions prior to submitting a claim to medicare. Web a cms 1490s form will be used by the centers for medicare and medicaid services. Print your medicare number exactly as it is shown on the medicare card. Web if you need to file your own medicare claim, you’ll need to fill out a patient request for medical payment form, the 1490s.
How To Fill Out A Medicare Application Form Ink
Form Cms1490s (Sc) Patient'S Request For Medical Payment printable

How To Apply For Medicare A And B

Medicare Claim Form 1490s Form Resume Examples a6Ynz58YBg

Medicare Form 1490s Instructions Form Resume Examples Wk9yGWvV3D
Medicare 1490s 20052024 Form Fill Out and Sign Printable PDF

CMS 1490S Form Patient's Request for Medical Payment FormSwift
Which Forms Are Used To Submit Medicare Claims

medicare cms 1490s claim form

Medicare Claim Form Cms 1490s Form Resume Examples bX5a6z2OwW
Please Read All Instructions Prior To Submitting A Claim To Medicare.
Web view / download form. Web the provided link below includes the form and all the applicable instructions. Web if you need to file your own medicare claim, you’ll need to fill out a patient request for medical payment form, the 1490s. This particular form is known as the patient’s request for medical payment form.
Filing A Claim When You Get Services And/Or Supplies (If Your Provider Doesn’t File It).
They must also attach any bill( s ) they received from providers/suppliers. Thank you for your recent request for the patient’s request for medical payment form. Web a cms 1490s form will be used by the centers for medicare and medicaid services. Send the form to the.
Print Your Medicare Number Exactly As It Is Shown On The Medicare Card.
Web print your name as shown on your medicare card (last name, first name, middle name). For all claims including influenza and pneumococcal vaccinations,. Web you’ll need the 1490s form if your doctor does not file a claim for you and you need to file it yourself what you’ll need: How to fill out this medicare form medicare will pay you directly when you complete this form and attach an itemized bill.
• Name, Medicare Number, And Address •.
Web 58 rows print your name as shown on your medicare card (last name, first name, middle name) print your medicare number exactly as it is shown on the medicare card;. Make sure it’s filed no later than 1 full. How to fill out this medicare. Fill out the patient's request for medical payment online and print it out for.