Cms1490S Printable Form
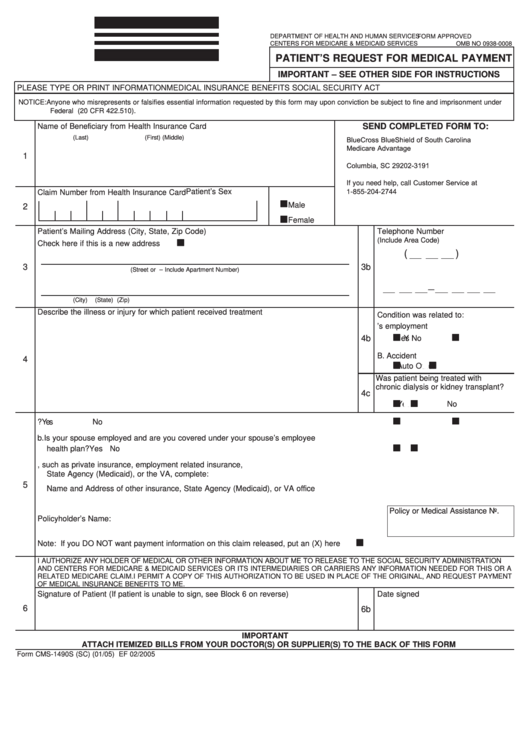
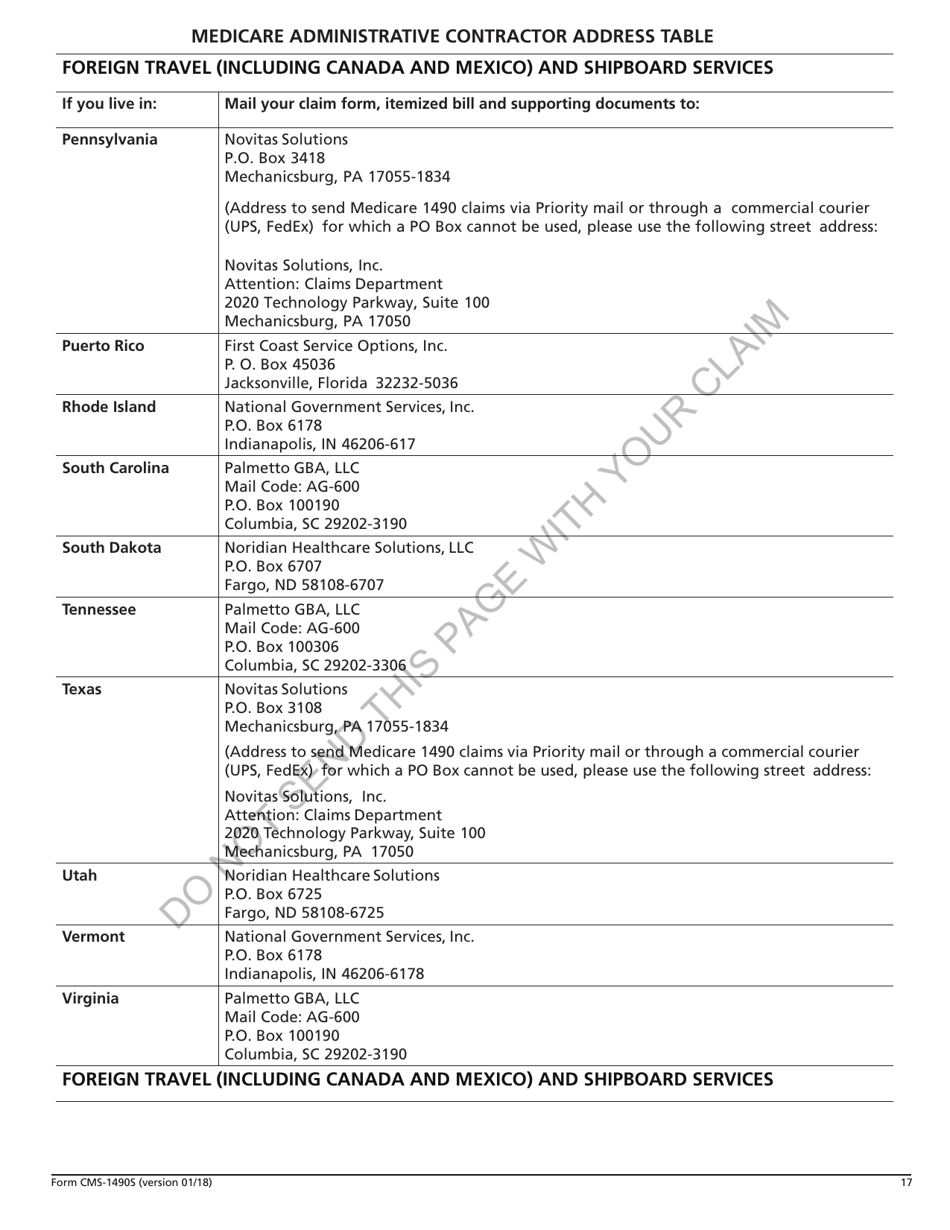
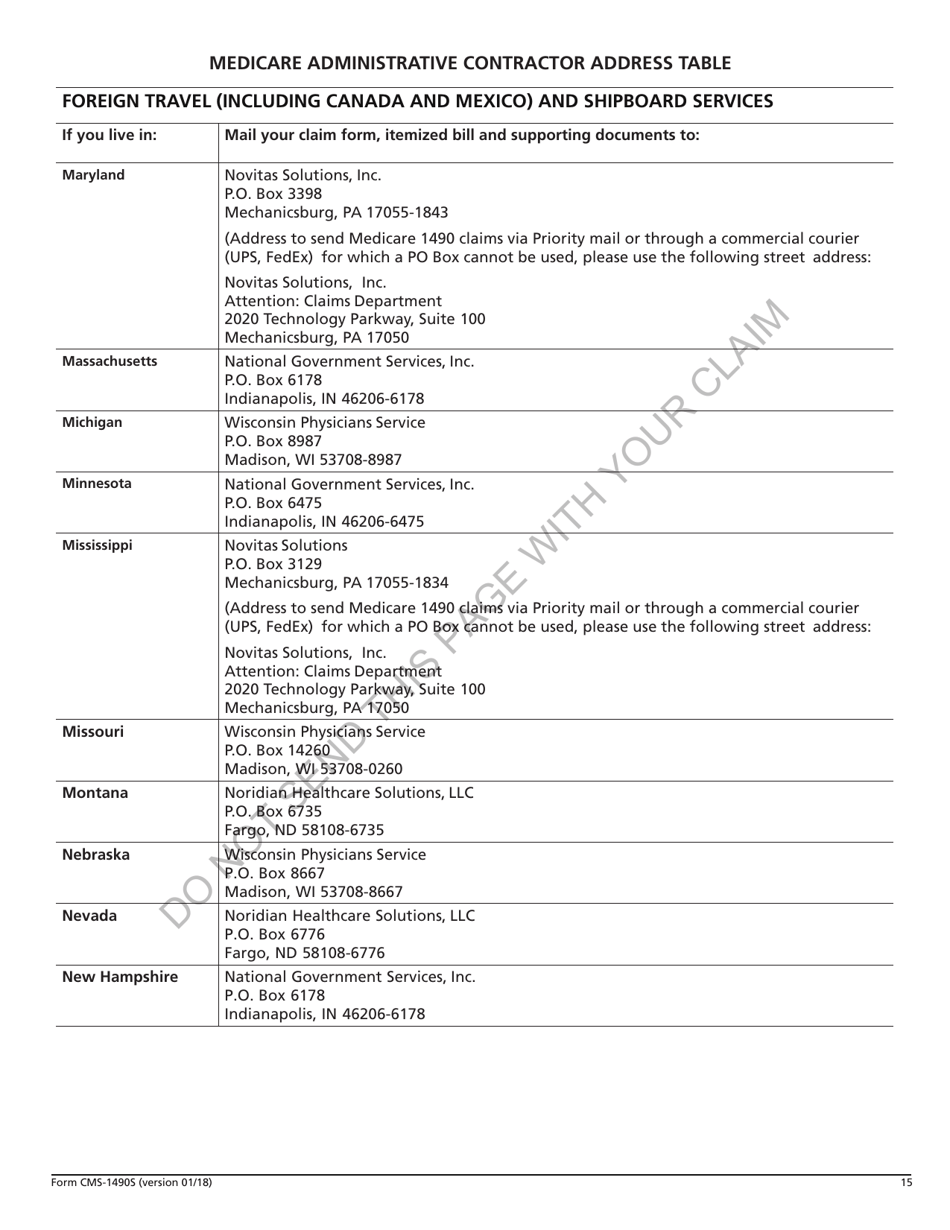
Cms1490S Printable Form - Hospital that can treat your medical condition, regardless of whether an emergency exists. Please read the attached instructions prior to submitting a claim. Web patient’s request for medical payment for the influenza/pneumococcal vaccinations, part b services, (includes physician, laboratory, imaging services), durable medical equipment, prosthetics, orthotics and supplies, foreign travel (including canada and mexico) and shipboard services. Follow the instructions for the type of claim you're filing (listed above under how do i file a claim?). Please read the attached instructions prior to submitting a claim to. Department of health and human services centers for medicare & medicaid services. Print out the form and instructions that apply to your situation (like for services you got on a cruise ship or during other foreign travel). Medicare can’t pay its share if the submission doesn’t happen within 12 months. Filing a claim when you get services and/or supplies (if your provider doesn’t file it). Print your health insurance claim number including the letter at the end exactly as it is shown on your medicare card.

Form CMS1490S Fill Out, Sign Online and Download Fillable PDF

Formulario CMS1490S Download Printable PDF or Fill Online Peticion Del
Form Cms1490s (Sc) Patient'S Request For Medical Payment printable
Form CMS1490S Fill Out, Sign Online and Download Fillable PDF
Fill Free Fillable Cigna Medicare Providers Pdf Forms 186

Form CMS1490S Fill Out, Sign Online and Download Fillable PDF
Form CMS1490S Fill Out, Sign Online and Download Fillable PDF
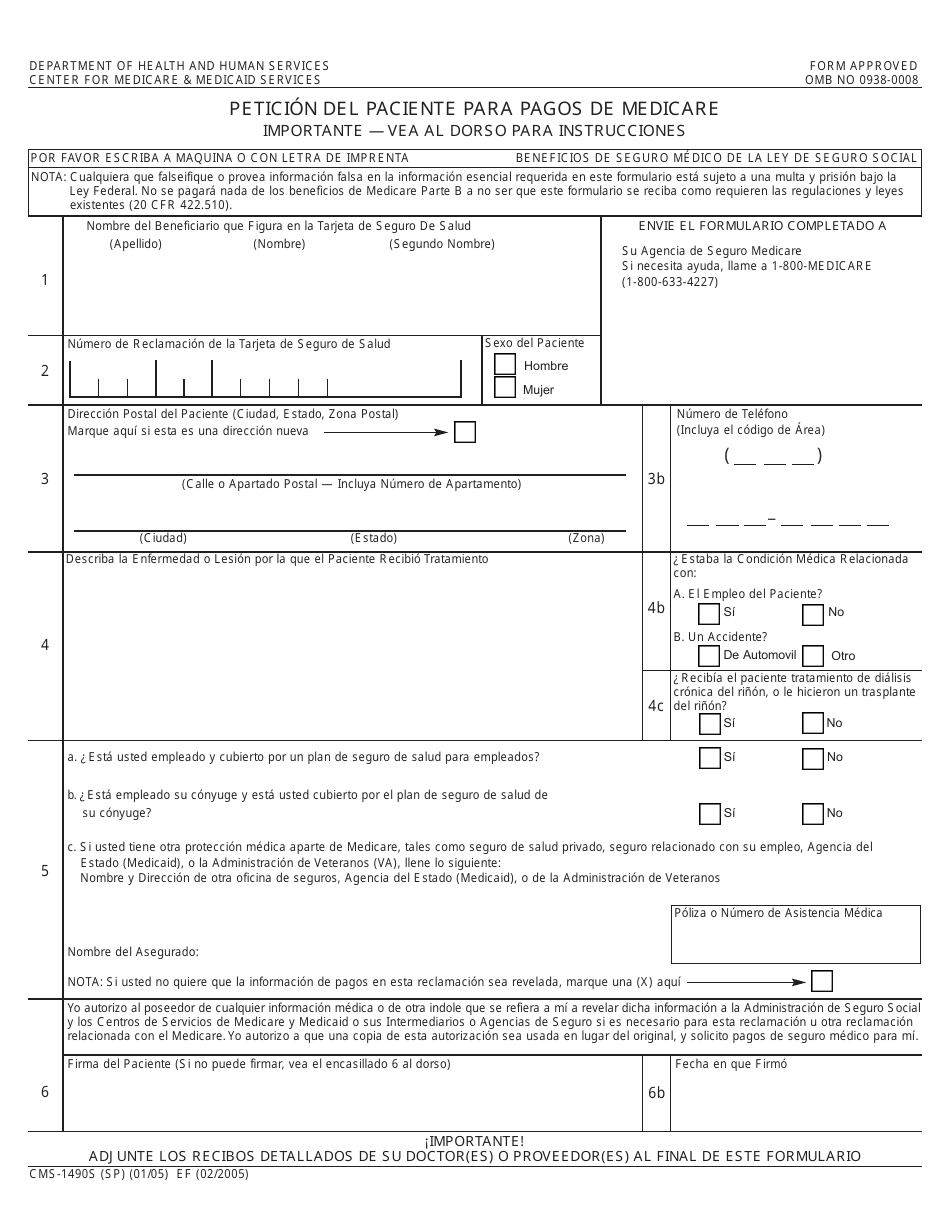
Formulario CMS1490S Download Printable PDF or Fill Online Peticion Del
medicare cms 1490s claim form
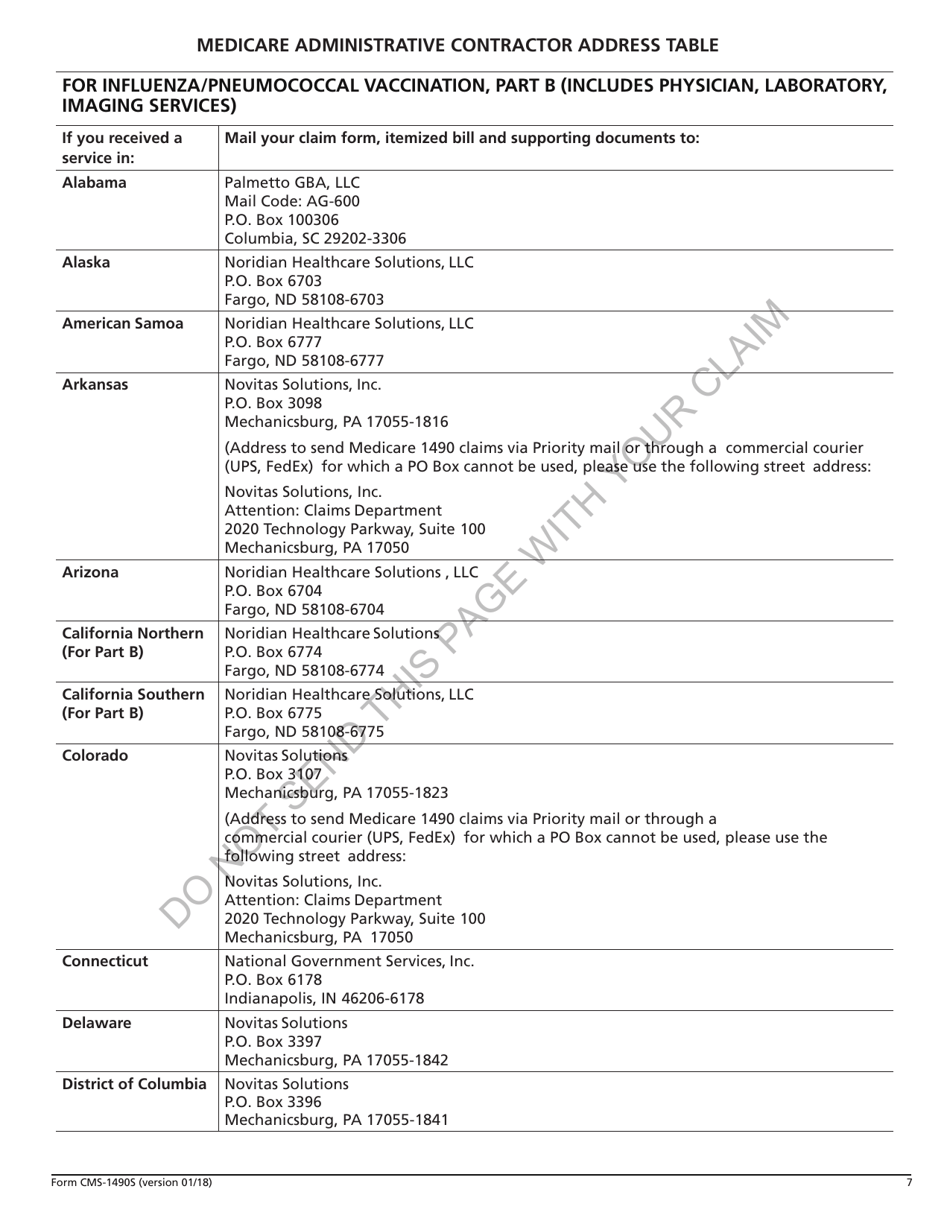
Form CMS1490S Fill Out, Sign Online and Download Fillable PDF
Print Out The Form And Instructions That Apply To Your Situation (Like For Services You Got On A Cruise Ship Or During Other Foreign Travel).
They must also attach any bill ( s) they received from providers/suppliers. Hospital that can treat your medical condition, regardless of whether an emergency exists. Medicare can’t pay its share if the submission doesn’t happen within 12 months. Make sure it’s filed no later than 1 full calendar year after the date of service.
Enclosed Is The Form, Instructions For Completing It, And Where To Return The Form For Processing.
Department of health and human services centers for medicare & medicaid services. Filing a claim when you get services and/or supplies (if your provider doesn’t file it). Patient’s request for medical payment. • inluenza (lu) or pneumococcal vaccinations • part b services (includes physician, laboratory, imaging services) • durable medical equipment, prosthetics, orthotics and.
Department Of Health And Human Services.
Please read the attached instructions prior to submitting a claim. Print your health insurance claim number including the letter at the end exactly as it is shown on your medicare card. Check the appropriate box for the patient’s sex. Choose the form/instructions combination that is appropriate for your situation:
Web A Cms 1490S Form Will Be Used By The Centers For Medicare And Medicaid Services.
Patient’s request for medical payment. Print your name shown on your medicare card (last name, first name, middle name). Follow the instructions for the type of claim you're filing (listed above under how do i file a claim?). What do i submit with the claim?