De 2501F Form Pdf Printable
De 2501F Form Pdf Printable - Web employment development department | california Web de 2501 form 2022 printable; In order to add an. • your physician/practitioner must complete the. Web about ca de 2501 2022 form. You must submit an original form provided by the edd, either electronically or through us mail. Select the document you want to sign and click upload. Web authorize any physician, practitioner, hospital, vocational rehabilitation counselor, orworkers’ compensation insurance carrier to furnish and disclose to employees ofcalifornia. Decide on what kind of signature to. Paid family leave form california;

Printable Form De 2501f Printable Form 2021

De 2501f Form Pdf Printable Printable Word Searches
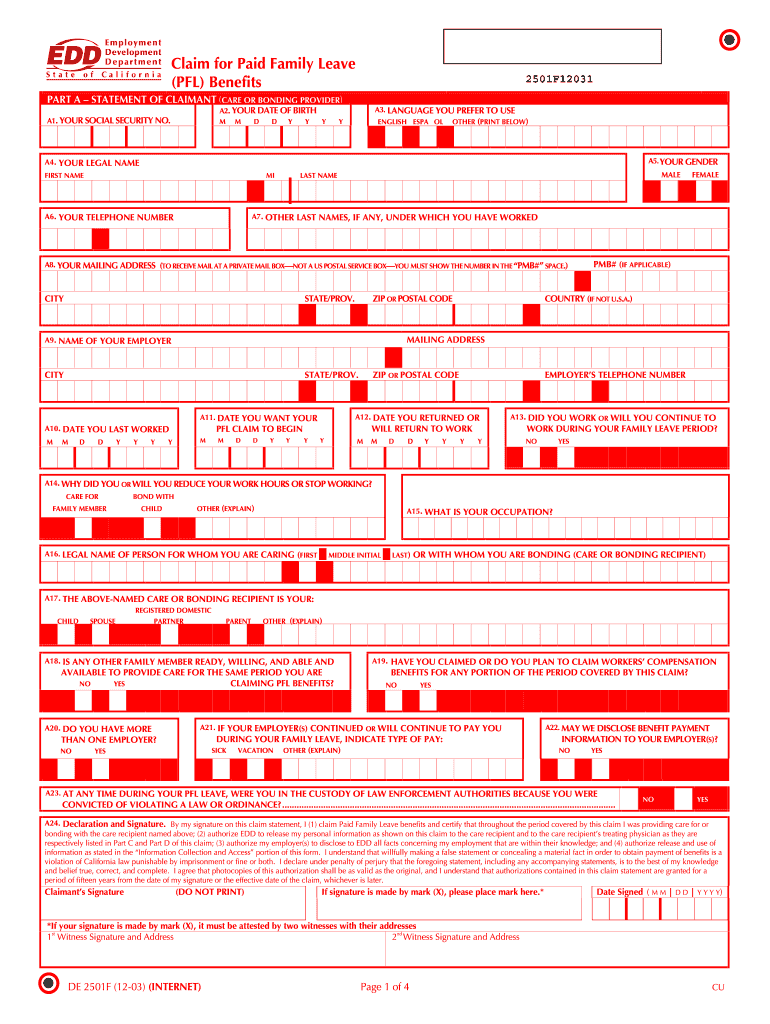
De 2501F Fill Out and Sign Printable PDF Template signNow

De 2501f Form Pdf Printable Printable Word Searches

Printable De 2501 Claim Form That are Hilaire Regina Blog
In Order To Add An.
Web employment development department | california Paid family leave form california; If you are not insured, you may also need to be able to pay your taxes or fees so make sure to contact your local tax collector for assistance. Web about ca de 2501 2022 form.
Web Use A De 2501F 2020 Template To Make Your Document Workflow More Streamlined.
Web • you must complete and submit a claim form within 49 days of the date you became disabled or you may lose benefits. Select the document you want to sign and click upload. You must submit an original form provided by the edd, either electronically or through us mail. Web do not complete these forms if you are a licensed physician or practitioner.
Web Authorize Any Physician, Practitioner, Hospital, Vocational Rehabilitation Counselor, Orworkers’ Compensation Insurance Carrier To Furnish And Disclose To Employees Ofcalifornia.
Web de 2501 form 2022 printable; Web de 2501 form 2021 pdf printablely find the app in the play market and install it for signing your claim for disability insurance di benefits de 2501 edd ca gov. Web claimant’s signature (do not print) if signature is made by mark (x), please place mark here.* date signed ( m m | d d | y y y y) *if your signature is made. • your physician/practitioner must complete the.
Get Form Show Details How It Works Upload The Family Paid Leave California Edit & Sign.
Decide on what kind of signature to.