Hipaa Form Printable
Hipaa Form Printable - The form must allow them to request their personal health information (phi) or grant a third party permission to release it. Check the applicable box to indicate to whom you authorize the release of your medical info. It also allows the added option for healthcare providers to share information. To fill out a hipaa release form, a patient must choose the appropriate document. Please complete all sections of this hipaa release form. Medical release forms include details about the information authorized for disclosure, its purpose, and the patient’s rights under the health insurance portability and accountability act of 1996 (hipaa). Free immediate download of medical relasese form pdf. I understand that by signing this consent i authorize you to use and disclose my protected health information to carry out: In the event the health information described below includes any of these types of information, and i initial the line on the box in item 8(a), i specifically authorize release of such information to the person(s) indicated in item 7. Direct free access to pdf of hipaa release.

HIPAA Consent Form Fill Out, Sign Online and Download PDF

Hipaa Fillable Form Pdf Printable Forms Free Online

Free Medical Records Release Authorization Forms (HIPAA)

FREE 8+ Sample Hipaa Release Forms in PDF MS Word

Free Printable Hipaa Authorization Form

Printable HIPAA Forms Complete with ease airSlate SignNow

FREE 11+ Sample HIPAA Forms in PDF MS Word

Printable HIPAA Consent Form Template Digital Download Editable Medical
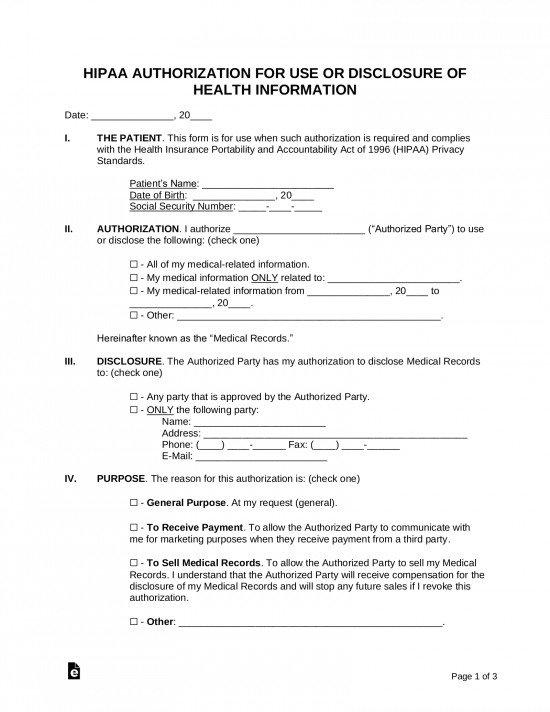
Free Medical Records Release Authorization Form (Waiver) HIPAA PDF

Printable HIPAA 20022025 Form Fill Out and Sign Printable PDF
These Rights Are Given To Me Under The Health Insurance Portability And Accountability Act Of 1996 (Hipaa).
Free immediate download of medical relasese form pdf. Medical release forms include details about the information authorized for disclosure, its purpose, and the patient’s rights under the health insurance portability and accountability act of 1996 (hipaa). In the event the health information described below includes any of these types of information, and i initial the line on the box in item 8(a), i specifically authorize release of such information to the person(s) indicated in item 7. I understand that by signing this consent i authorize you to use and disclose my protected health information to carry out:
Check The Applicable Box To Indicate To Whom You Authorize The Release Of Your Medical Info.
Please complete all sections of this hipaa release form. The medical record information release (hipaa) form allows patients to give authorization to a 3rd party and access their health records. The form must allow them to request their personal health information (phi) or grant a third party permission to release it. To fill out a hipaa release form, a patient must choose the appropriate document.
How To Fill Out A Hipaa Release Form.
It also allows the added option for healthcare providers to share information. This form is for use when such authorization is required and complies with the health insurance portability and accountability act of 1996 (hipaa) privacy standards. If any sections are left blank, this form will be invalid and it will not be possible for your health information to be shared as requested. I understand that i have certain rights to privacy regarding my protected health information.
Powers Granted Under A Medical Release Can Be Revoked Or Reassigned At Any Time.
Direct free access to pdf of hipaa release.