Printable Ub04 Form
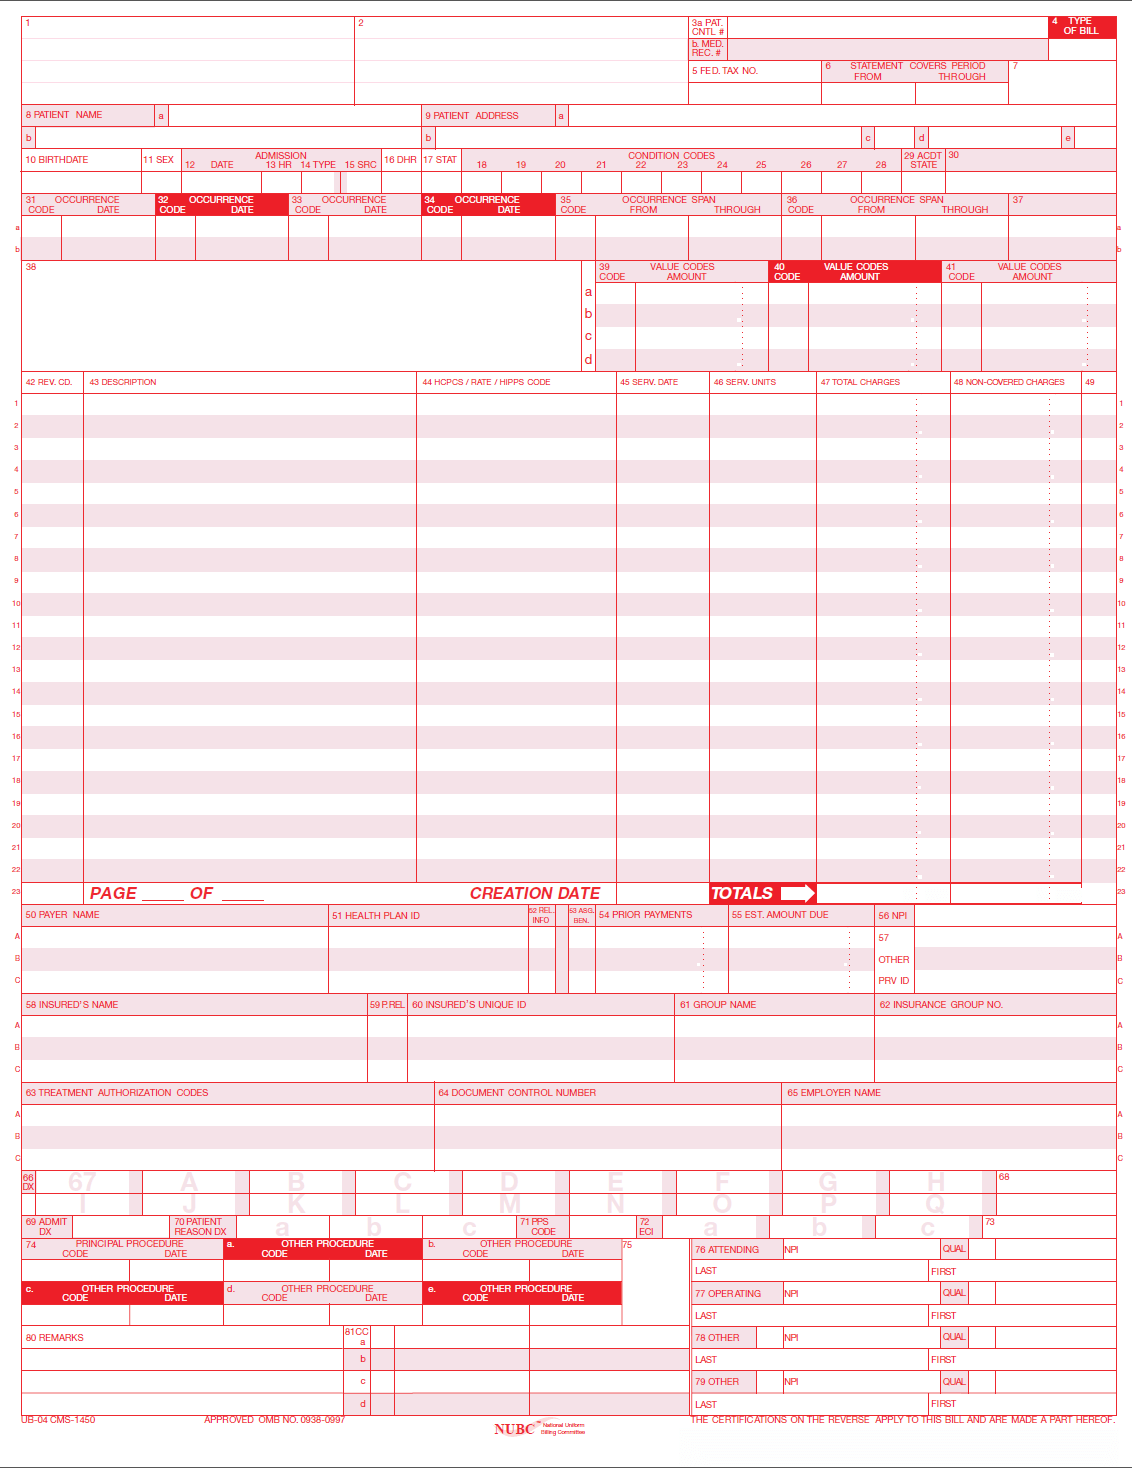
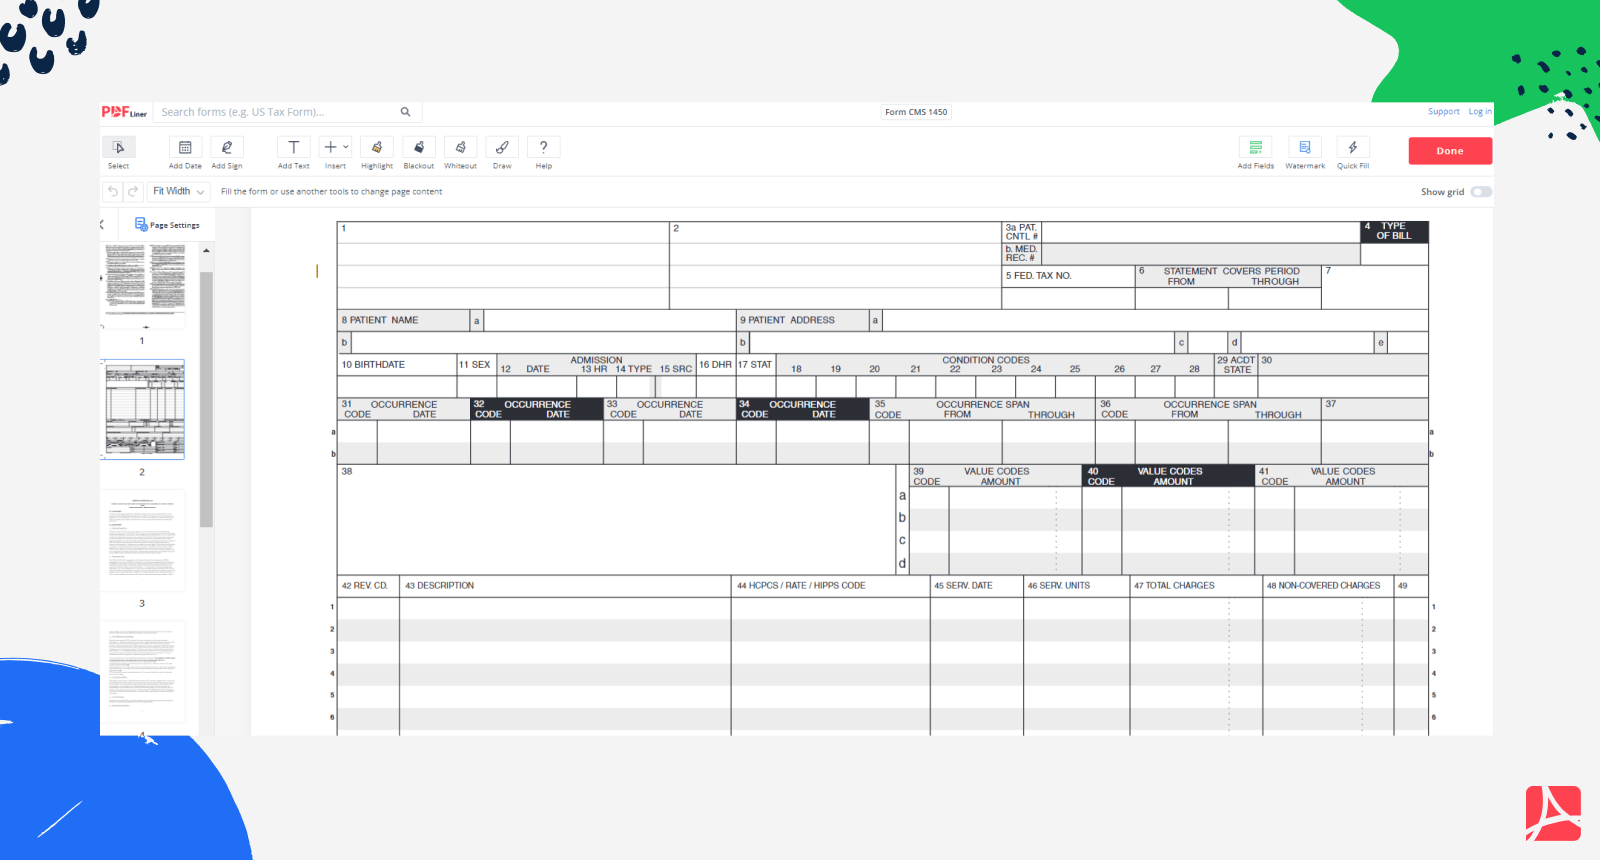
Printable Ub04 Form - Web the ub04 claim form is used to submit claims for inpatient and outpatient services by institutional facilities (for example, outpatient departments, rural health clinics, chronic. We are providing two different versions in. Web patient control number enter your facility's unique account number assigned to the patient, up to 20 alpha/numeric characters. Enter the name and address of the hospital/facility submitting the claim. Web of essential information as requested by this form, may serve as the basis for civil monetarty penalties and assessments and may upon conviction include fines and/or. This number will be printed on the ra and will help. Billing provider name & address. Enter the billing provider’s name, street address, city, state, and zip code where the services were performed. Online customers supportpaperless workflowfree trialcancel anytime Enter the billing provider’s mailing.
Free Fillable Ub 04 Claim Form Printable Forms Free Online
Download UB04 Claim Form PDF wikiDownload
Ub 04 Form Tricare Bill Form printable pdf download
UB04 Form or CMS 1450 Print and sign form CMS 1450 online — PDFliner

UB04CF UB04 Hospital Claim Form
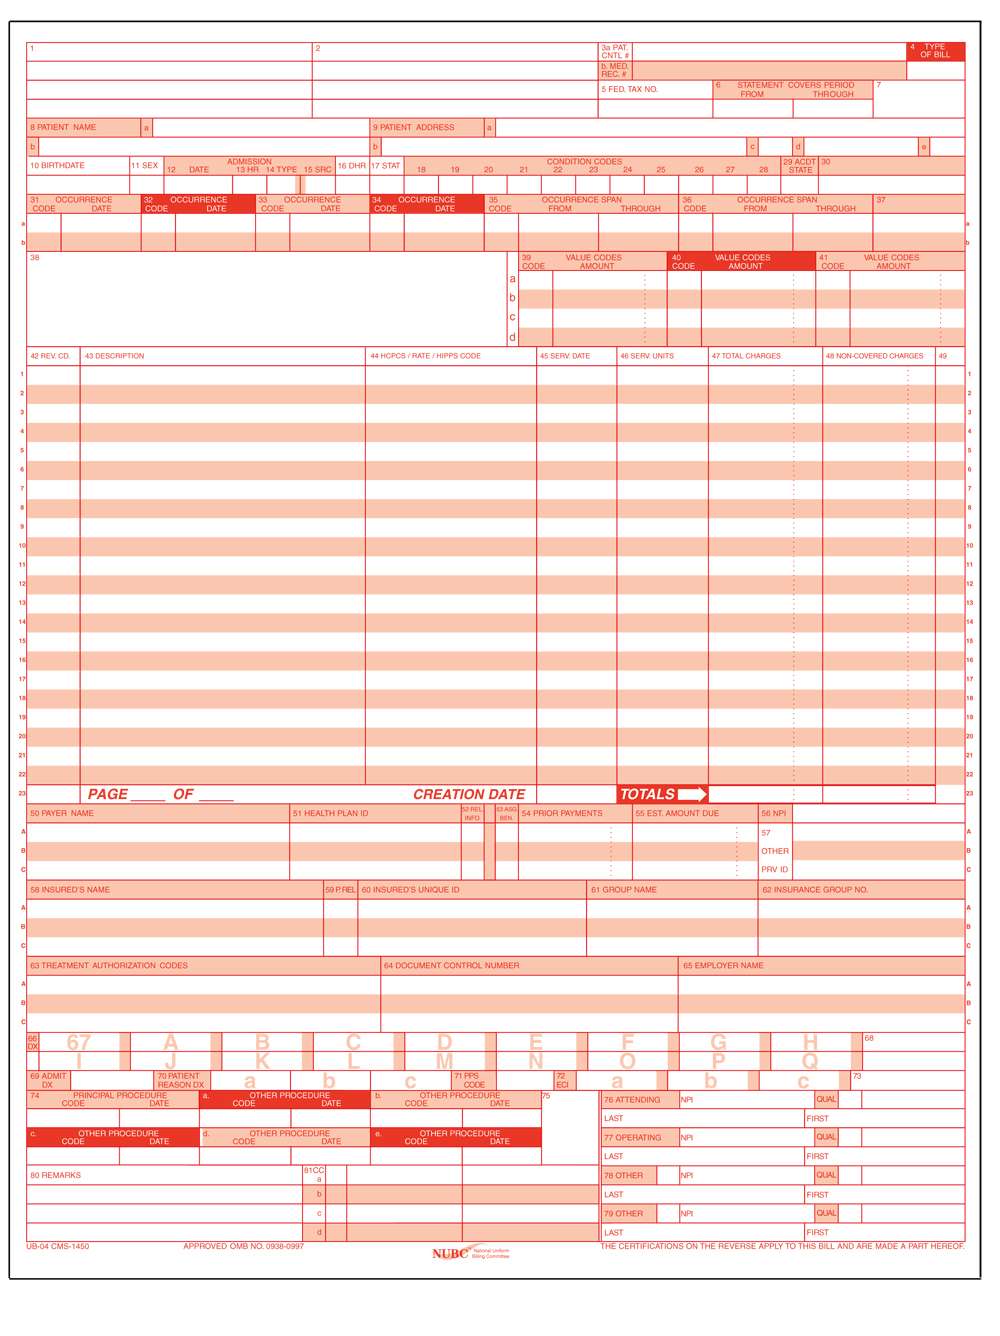
Free Fillable And Printable Ub 04 Claim Form Printabl vrogue.co
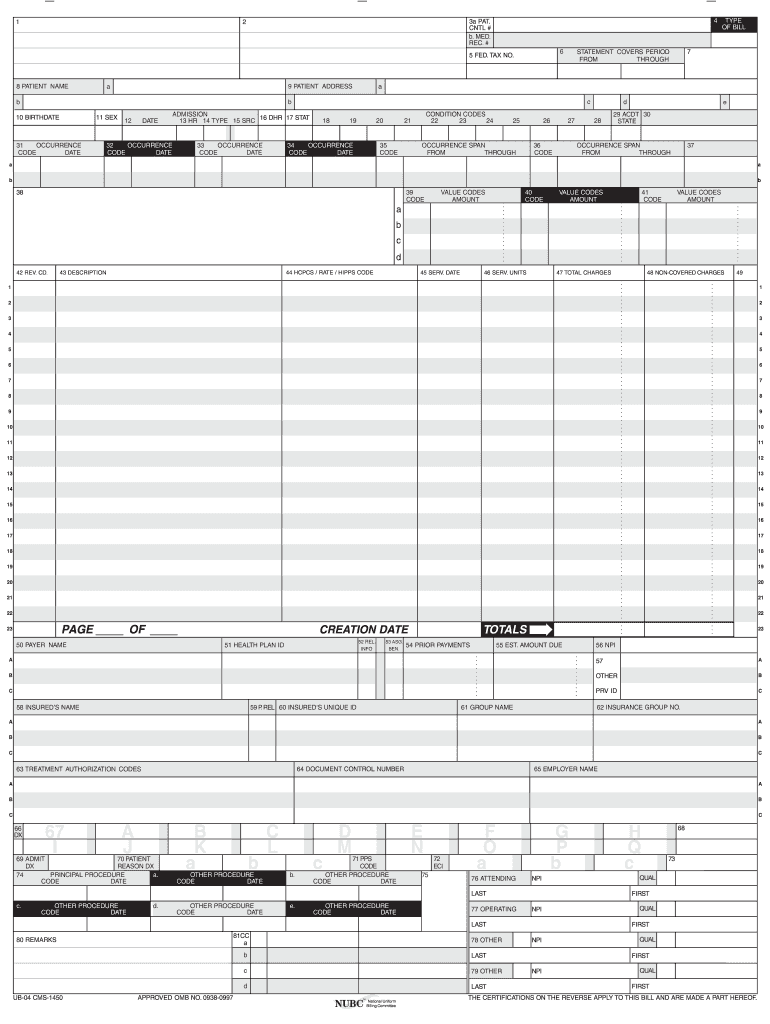
NUBC UB04 CMS1450 Fill and Sign Printable Template Online US Legal
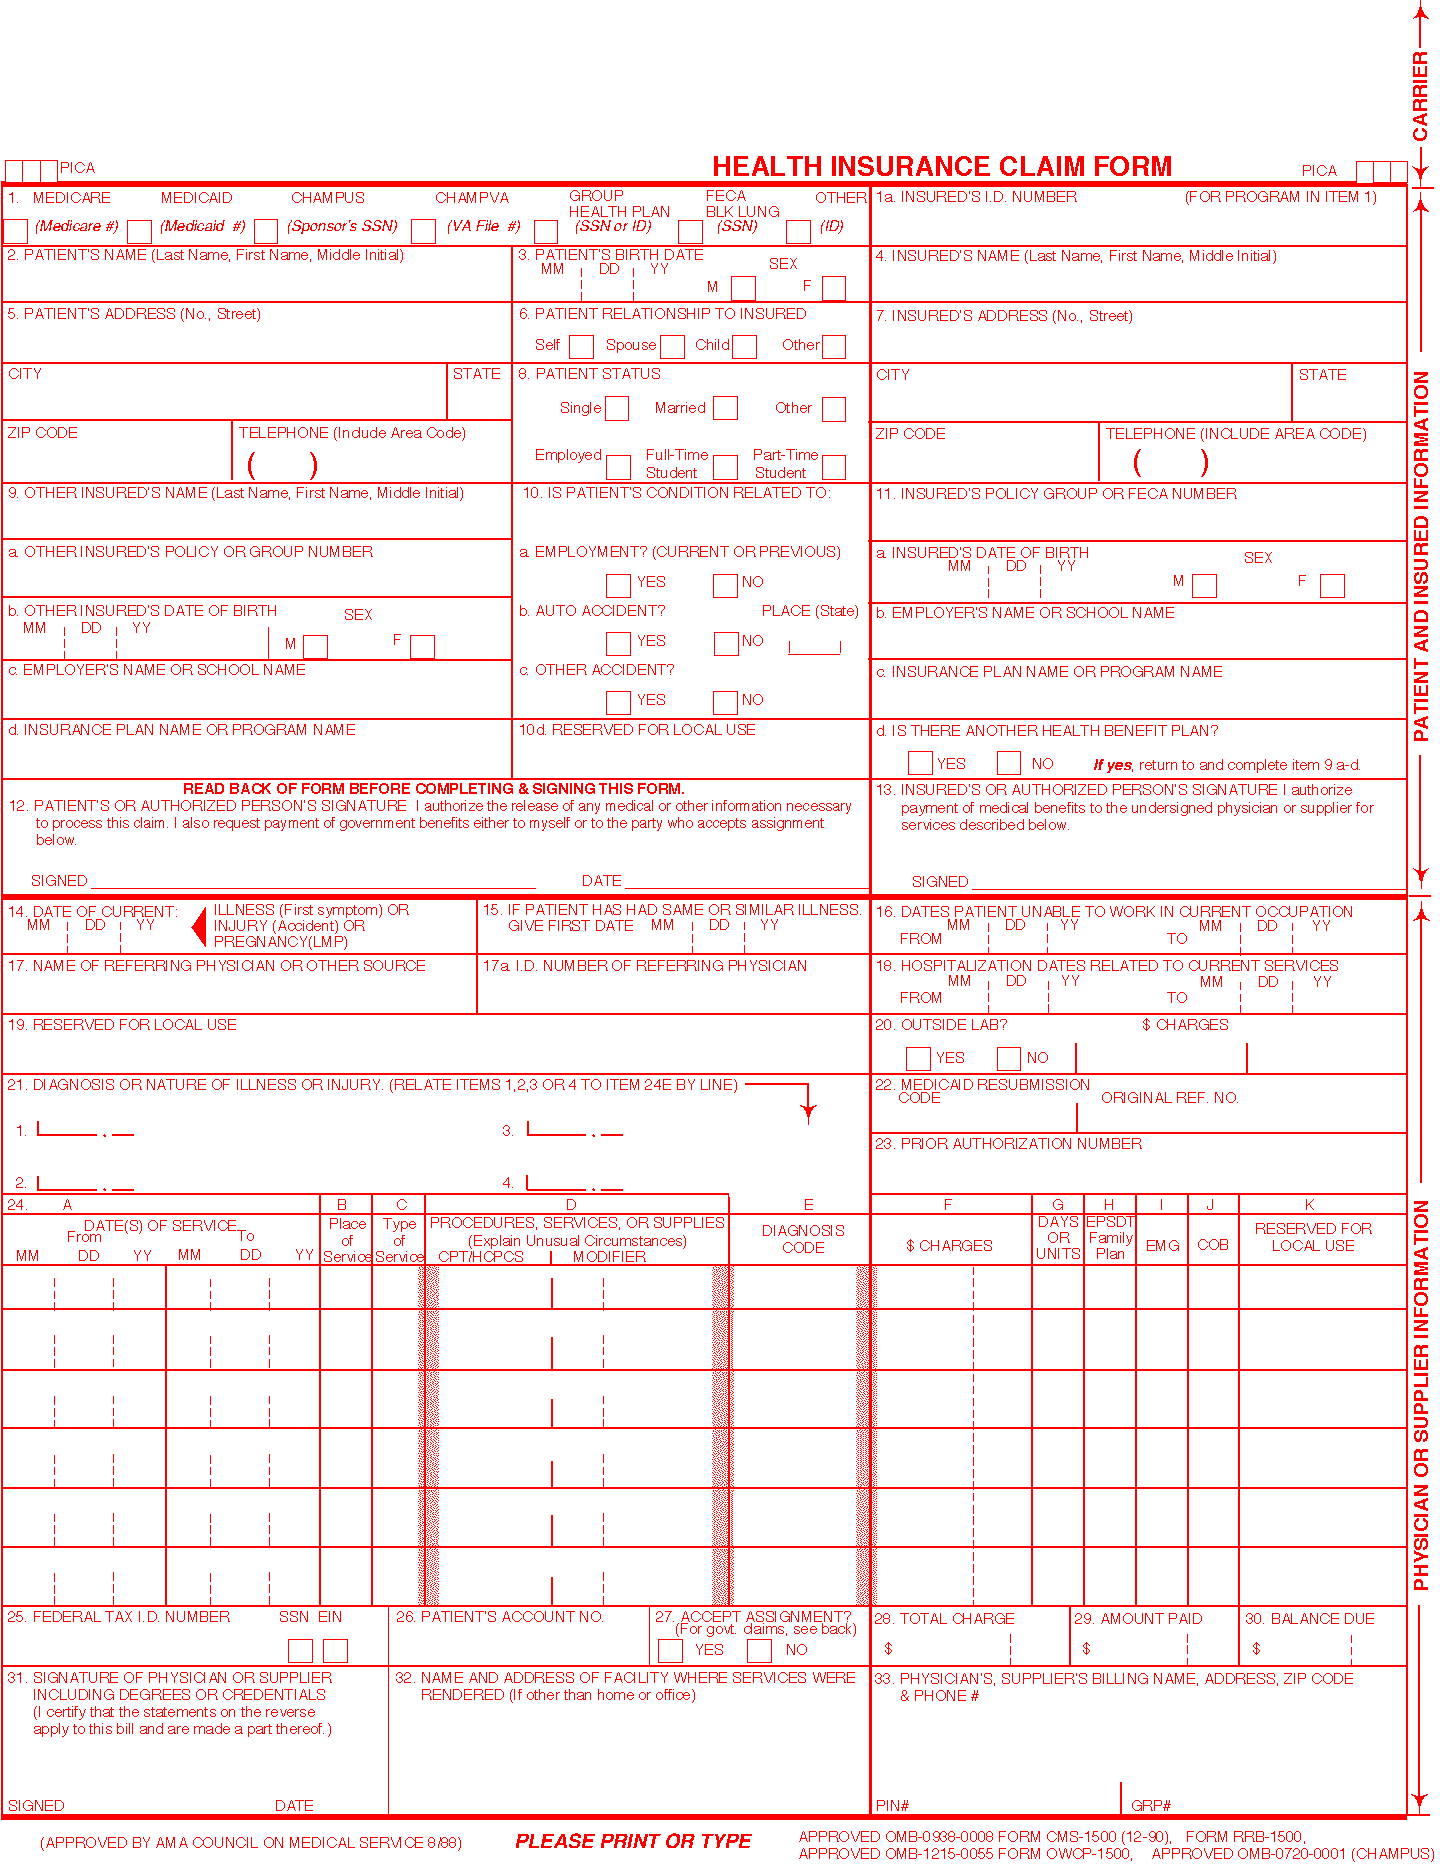
Ub 04 Fillable Template Master of Documents
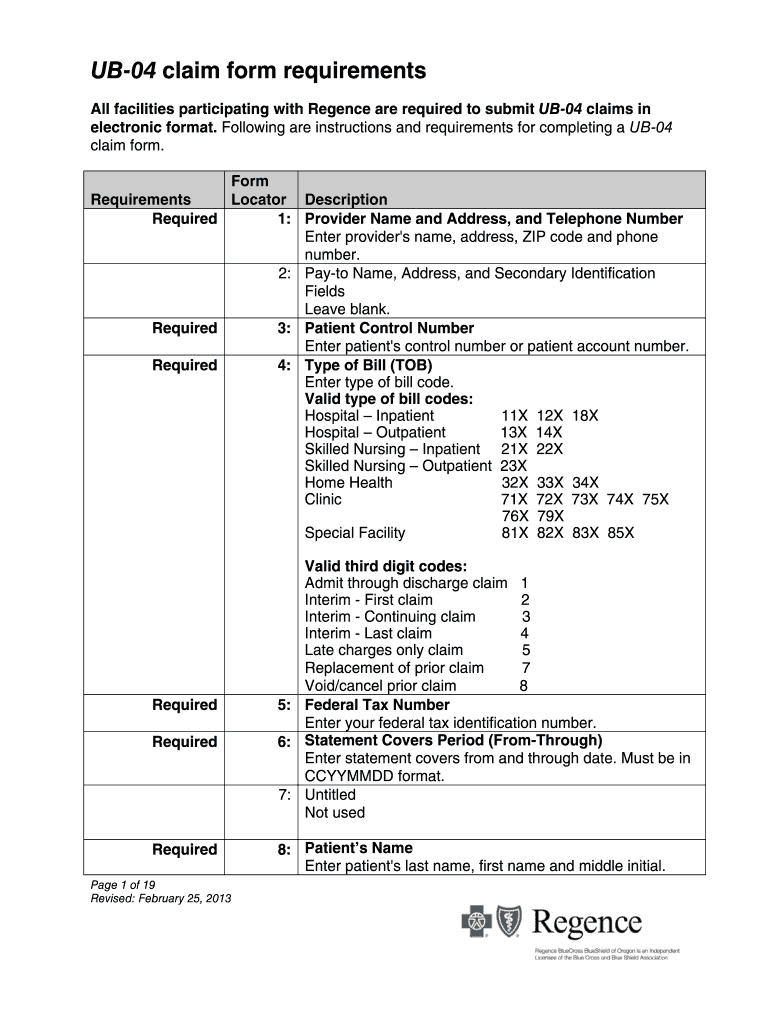
Ub04 Ms Word Form Fill and Sign Printable Template Online US Legal
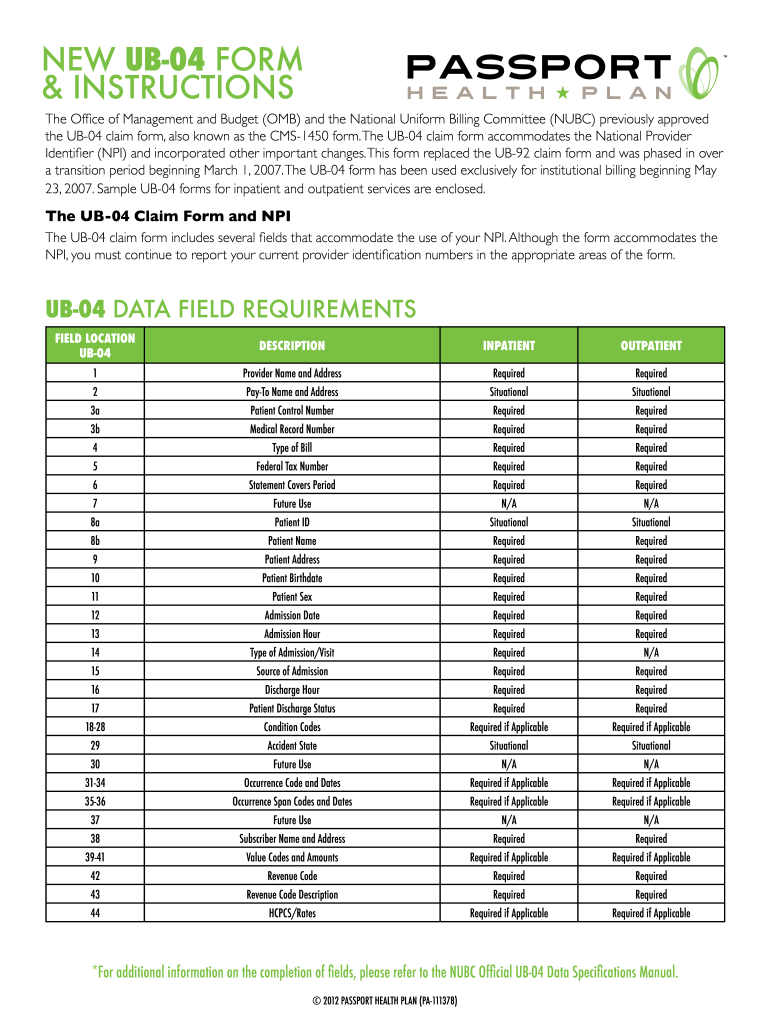
Blank Ub 04 Claim Form Printable
Enter The Name And Address Of The Hospital/Facility Submitting The Claim.
Web learn how to fill out the ub04 form for health insurance claims with this online tutorial from mcgraw hill education. You can fill in the attached forms electronically, using adobe form filler, as long as you have adobe acrobat reader. Online customers supportpaperless workflowfree trialcancel anytime Web patient control number enter your facility's unique account number assigned to the patient, up to 20 alpha/numeric characters.
We Are Providing Two Different Versions In.
Billing provider name & address. Web the ub04 claim form is used to submit claims for inpatient and outpatient services by institutional facilities (for example, outpatient departments, rural health clinics, chronic. Enter the billing provider’s name, street address, city, state, and zip code where the services were performed. This number will be printed on the ra and will help.
Web Of Essential Information As Requested By This Form, May Serve As The Basis For Civil Monetarty Penalties And Assessments And May Upon Conviction Include Fines And/Or.
Enter the billing provider’s mailing. • inpatient hospital facilities, such as medical/surgical intensive.